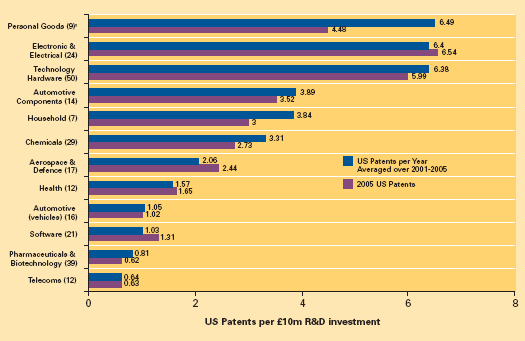Tuesday, November 14, 2006

Access to Medicine Ongoing Challenge for Poor


Oxfam has released today a Briefing Paper outlining how very little has changed to improve access to medicines since Doha. In the press release accompanying the publication, Oxfam says, "Poor people in developing countries are still being denied life-saving medicines five years after world leaders signed a formal trade declaration to put health before profits."

The Briefing Paper, entitled "Patents versus Patients: Five years after the Doha Declaration," maintains that trade rules continue to present a major barrier to genuine access to affordable medicines. The Paper describes patent protection as an ongoing obstacle to the delivery of cheaper generic versions to poor countries and calls for urgent action.

The Paper states "The Doha Declaration unequivocally recognises and clarifies that the TRIPS Agreement should not prevent WTO member countries from taking measures to protect public health," and "recognises the legitimate need of countries to take measures to reduce the price of medicines, such as using TRIPS safeguards." However, the "TRIPS-plus agenda" is seriously compromising the availability of such flexibilities and safeguards. In particular, the Briefing Paper criticises US trade policy and the emphasis on bilateral and regional free trade agreements as a way to ensure strong intellectual property protection despite the commitment to public health in the Doha Declaration. This is combined with what the paper describes as the indifference of other rich countries, where "all pharmaceutical companies selling medicines in a developing country, including European countries, benefit ... essentially 'free-riding' on US efforts to introduce TRIPS-plus rules."

The paper calls for new ways to promote patients over patents, noting the World Health Assembly Resolution of 2006 which established the inter-governmental working group. The World Health Organization (WHO) is tomorrow completing a public hearing in preparation for the meeting of the working group. Oxfam's paper focuses on several important cases, including the Glivec controversy.

The International Federation of Pharmaceutical Manufacturers & Associations (IFPMA) was reported in Reuters today as arguing that access to medicines is not the major public health issue in the developing world, but rather inadaquate infrastructure. But Ellen 't Hoen of Medecins sans Frontieres (MSF) was quoted as saying "The current system based on patents and high prices to pay for innovation leads to rationing and leaves huge health needs neglected."

Oxfam is currently launching the Briefing Paper at BMA House in London, with highlights to be published at Patents vs Patients: Whose Rights Come First?

Saturday, November 04, 2006

Call for Papers - Special Journal Issue


Call for Papers
Special Issue September 2007
Intellectual Property, Medicine and Public Health

Deadline: 1 June 2007

This is a call for papers for a special issue of SCRIPT-ed, entitled “Intellectual Property, Medicine, and Public Health”

This issue will be dedicated to the discussion, analysis, and consideration of the inter-relationships of public health, intellectual property, and medical and pharmaceutical industry.

Submissions of short analysis pieces (up to 1000 words), longer analysis pieces (approximately 1000 to 3000 words), peer-reviewed articles, and student papers are invited.

All papers dealing with relevant topics and discussions will be considered, but some suggested areas of interest may include:

* access to medicines

* trade, bilaterals, and public health

* development

* gene sequences and patent law

* biopharmaceuticals

* patents and innovation

* data exclusivity

* stem cells

* property in human tissue

* genetic databases

* traditional knowledge and genetic resources

* more …


Informal enquiries may be made by email to the Guest Editor, Dr Johanna Gibson

Submissions by 1 June 2007 may be made by email to the Guest Editor, Dr Johanna Gibson or by mail to:

Dr Johanna Gibson
QMIPRI
Centre for Commercial Law Studies
Queen Mary, University of London
John Vane Science Centre
Charterhouse Square
London EC1M 6BQ
UNITED KINGDOM

Friday, November 03, 2006

WHO Public Hearing - Engaging the Private for Urgent Public Good


The World Health Organization (WHO) is currently conducting an online Public Hearing to collect data and proposals from various stakeholders and actors, towards an analysis of intellectual property rights, innovation and public health. Running 1-15 November, the Public Hearing will accept contributions from a wide range of stakeholders and actors.

The contributions to the Public Hearing will be collected for the first official meeting (4-8 December) of the intergovernmental working group (IGWG), convened under Resolution WHA59.24, "Public health, innovation, essential health research and intellectual property rights: towards a global strategy and plan of action." Resolution WHA59.24 was adopted at the 59th World Health Assembly, after consideration of the recommendations of the WHO Commission on Intellectual Property Rights, Innovation and Public Health (CIPIH), which concluded with its report in April 2006.

The IGWG is open to all interested Member States, and IP-Watch reports that the WHO will also invite a wide range of observers, UN organisations, intergovernmental and nongovernmental organisations, as well as experts and selected public and private entities.

The IGWG will collect the data and proposals from various stakeholders through this Public Hearing and prepare an analysis of intellectual property rights, innovation and public health, to be submitted to the 61st World Health Assembly, to be held in May 2008. This analysis will develop a global strategy for sustainable needs-driven health research and development, with particular attention to those diseases affecting developing countries.

Some of these major diseases are those caused by helminth infections. Earlier this month, the WHO published guidelines on Preventive Chemotherapy in Human Helminthiasis, examining large-scale prevention and treatment programmes in helminth infections causing schistosomiasis or bilharzia, diseases which are disproportionately high in developing countries. The manual sets out the new strategy to fight these infections, involving a partnership of more than 25 organisations. As well as a significant public health concern, the WHO has also identified serious considerations with respect to human rights, in that sufferers are often ostracised and stigmatised as a result of these infections and the effects on the body. In the accompanying press release to the publication, Dr David Heymann, WHO Acting Assistant Director-General for Communicable Diseases, said that treatment and prevention of these diseases is urgent and "incontestable from all perspectives: moral, human rights, economic and global public good. The task is feasible and must be done."

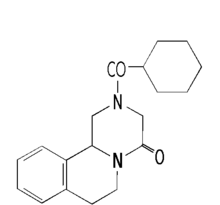
Pharmaceutical companies and private donors "make good the gap" in delivering the support to poorer countries, as reported in the Financial Times (FT) earlier this month. According to the FT, all the drugs required for these are diseases are donated, except Praziquantel (for the treatment of bilharzia, formula at right). Merck manufactures the drug, and Bayer markets the drug for veterinary use. WHO has been in negotiations with both for some time, but to date there had been no agreement to provide the drug.

However, Merck is now co-operating with the WHO towards the production by 2008 of drugs to treat bilharzia at less than half the market cost, following reports of increased "pressure" on Bayer and Merck to donate "for human use a drug they sell for pets." Professor Lorenzo Savioli, Director of the WHO Department of Control of Neglected Tropical Diseases, said to the FT that the renewed action and fresh requests to the companies are in response to "a real market failure because schistosomiasis affects the poorest of the poor. But Bayer tells us to talk to Merck, and Merck says talk to Bayer."

The FT reports that Merck was approached by the WHO early this year in Spring, but that supplies were presently too small and production costs too high to allow for a viable mechanism to supply the drug at the costs and quantities required.

The FT also reports that Bayer originally helped develop praziquantel with WHO support in the 1970s for the treatment of patients in Africa. However, Bayer concluded that it could not produce the drug so that it would be affordable. Bayer's public profile, much maligned following the GM contamination of US rice imports, is unlikely to be assisted by what the FT reports as its reluctance to participate in initiatives to achieve distribution of the drug in Africa.

Meanwhile, Pfizer is providing open access to its library of 3 million chemical compounds to WHO-affiliated researchers on tropical diseases. Initially, access was granted to 12 000 compounds for the treatment of helminth infections and related concerns. The intellectual property rights arising from such programmes, however, are not clear, as no decision has been made on what will happen to any promising developments.

Tuesday, October 31, 2006

UK R&D Scoreboard 2006 - GSK Lifts UK R&D, But Size Does Matter


The UK Department of Trade and Industry (DTI) has just released the figures for the 2006 R&D scoreboard.

The R&D Scoreboard 2006 provides information on the top 800 UK and top 1250 global companies based on R&D investment. The meaning of R&D for the Scoreboard is found in the UK in the Standard Statement of Accounting Practice (SSAP 13), which defines the concept based on the different definitions used by the Organisation for Economic Co-operation and Development (OECD) Frascati manual on expenditure for research and development. For global companies the International Accounting Standard (IAS 38) is used, also based on the Frascati manual.

The SSAP provides the definition of expenditure falling into one or more of the categories of pure or basic research, applied research, and development. The third category is particularly relevant to associated measurements of patent activity, in that it covers the "use of scientific or technical knowledge in order to produce new or substantially improved materials, devices, products ..."

72 UK companies made it into the Global 1250, with an increase in UK R&D expenditure (including 245 foreign owned companies) to £19.2bn (£17bn in 2005). This has been attributed to greater disclosure as well as an increase in R&D, which is particularly strong in pharmaceuticals in the UK. The previous decrease in UK 800 expenditure (1% decrease in 2005) has been replaced by an increase of 4% in 2006. GlaxoSmithKline (GSK) reported one of the larges, at £297million.

But others have criticised the increase as "distorted," pointing to the new accounting rule that insists on greater levels of disclosure in sectors not traditionally driven by or associated with R&D, such as banking. DTI senior industrialist and lead author of the report, Mike Tubbs (pictured right), in a report in The Independent, said "For the first time we had R&D from these companies. We knew they did R&D but we did not know it was that much." But a report in The Times suggests instead that "Britain is losing ground."

The Scoreboard for the Global 1250 shows that the pharmaceutical sector (along with software) is one of the fasting growing sectors with highest profitability. But it is second place in R&D, just behind technology hardware, putting 6 pharmaceutical companies in the top 20 (compared to none just 10 years ago). However, the number of patents granted per £10million is much lower than those for technology hardware and electronics.

The patent-to-R&D ratio for 12 sectors

According to the Scoreboard, around a quarter of the Global 1250 companies are mid-sized (sales of £50-500 million) with pharmaceutical companies making up 3/4 of these. Pharmaceuticals are the dominant sector in the UK, with the UK having the second largest proportion of pharmaceutical companies of all the top 7 R&D countries (with US having the greatest). Because the UK is particularly strong in pharmaceuticals, the report states that this explains why the UK does not have any companies in the top 20 for 2005 US patents.

Although the centenarian, GSK, is now the second-largest pharmaceutical company in the world (behind Pfizer), but a report in today's IP-Watch suggests that there is a distinct market advantage for small and medium-sized pharmaceuticals (SMEs) when it comes to neglected diseases and diseases in developing countries. Reporting on a seminar at the headquarters of the World Intellectual Property Organization (WIPO), co-organised with the Stockholm Network, IP-Watch notes the importance of "creative licensing deals" and cooperation with larger pharmaceutical companies. On patenting, Nikolaus Thumm, senior economic counsellor of the Swiss Federal Institute of Intellectual Property, told the meeting that there is a need to correct the "common misunderstanding" that the stronger the protection, the more innovation.

Thursday, October 26, 2006

Free Public Workshop - London, 13 November 2006

Criminal Enforcement Directive

Let the Punishment Fit the Crime?


The Patenting Lives network will be conducting a free public workshop on the proposed European Directive on criminal measures aimed at ensuring the enforcement of intellectual property rights (Criminal Enforcement Directive).

The workshop will commence with a discussion by a panel of experts, looking at the possible implications of the Directive for patentable technologies and patent practice.

Expert Panellists

Gwilym Roberts, Partner, Kilburn & Strode Patent Attorneys

Julian Heathcote Hobbins, Senior Legal Counsel, FAST (Federation Against Software Theft)

Phillip Johnson, Barrister, DTI Legal Services, Legal Adviser to the UK Patent Office

(Chair Johanna Gibson)

The event will commence at 6pm, 13 November 2006, and will be held at the Centre for Commercial Law Studies (CCLS) in the QMIPRI Seminar Room, John Vane Science Centre, Charterhouse Square, Queen Mary University of London (map).

The workshop is FREE but numbers are limited, so please register by email to Johanna Gibson.

This is the first in a series of Patenting Lives public workshops on current issues in patent law. Stay tuned for more to come.

For more details on the Patenting Lives project and network, please visit patenting lives or the patenting lives blog

Wednesday, October 25, 2006

Competition Inquiry into Johnson / Pfizer Deals


The European Commission has commenced a competition inquiry into Johnson & Johnson's planned acquisition of Pfizer's consumer health interests.

The Commission's Competition Directorate will decide at the end of next month whether the sale can proceed or whether a full-scale investigation is warranted. If the latter route is taken, this will delay the process by a further 90 days.

The proposed deal was announced in June this year and will result in Johnson & Johnson having a substantial monopoly over consumer health products. Jonathan Todd, speaking for the Commission's Competition Directorate, was quoted in an article in The Times saying, "Our concern is whether or not there may be an adverse effect on consumers, pricing and competition."

Earlier this month it was reported that US anti-trust regulators forced Johnson & Johnson and Pfizer to agree to sell Zantac (to Boehringer-Ingelheim Pharmaceuticals, for US$509.5M), after there were concerns that this product overlapped with some Pfizer products.

Meanwhile, as reported in the Financial Times last week, Lloydspharmacy has asked the Office of Fair Trading (OFT) in the UK to investigate Pfizer's exclusive agreement with UniChem to act as a single distributor for its drugs in the UK. UniChem is part of Alliance Boots, which also runs the large rival pharmacy chain, Boots.

Pfizer claims that the deal is to control the supply chain in a fight against counterfeit drugs, but after the expiration of patent protection for several of its key sellers - including Zythromax (antibiotic), Diflucan (antifungal), and Zoloft (antidepressent) - the agreement seems to be equally about limiting competition from cheaper, generic versions. Other British pharmacies and drug distributors are concerned that this will lead to an anti-competitive monopoly, adversely affecting consumers with higher prices. According to a recent report in the Financial Times, Pfizer's drugs account for around 15% of the UK's £10.3 billion pharmaceutical market. Furthemore, pharmacies will be forced to use UniChem as the exclusive provider of Pfizer's branded drugs, leading to concerns that Pfizer will be able to control the discounts available to retailers as well.

James Harding, in an opinion piece in the The Times, suggests that public scrutiny will exonerate Pfizer, but he is correct to note that important questions being asked, "Is Pfizer just hyping up the counterfeits argument in order to cut out competition and take control of pricing?" and "Will UniChem provide as reliable a service to other pharmacies as it does to its own Boots stores?" In other words, the Pfizer-UniChem agreement will in effect control each level of the chain, right down to the deals with individual retailers themselves. By "taking a risk," Harding seems to think Pfizer is exonerated. But surely that is the nature of the entrepreneurial business models - taking risks pays much higher dividends. It is not clear that the risk of Pfizer grazing a knee if UniChem stumbles will be a sufficient check and balance against the potentially anti-competitive nature of this deal.

The British Association of Pharmaceutical Wholesalers (BAPW), the main trade body in the UK, is likely to make a similar complaint with the OFT. The Chairman of BAPW, Ian Brownlee, said to The Times, "With a single supplier the delivery system cannot ensure that pharmaceutical products are there in the dispensary when they are needed. Profit is being put before patient safety with a breathtaking arrogance." UniChem is one of its members.

Monday, October 23, 2006

EU Council Adopts EC Regulation on Paediatric Medicines


The Council of the European Union (EU) announced today that it has adopted the EC Regulation on medicinal products for paediatric use.

Today's press release states that the new Regulation aims to improve child health, as considered in more detail in earlier background material accompanying the original proposal. The Regulation sets out specific requirements for the authorisation and use of medicines in children, in response to a concern that around 50% of medicines used to treat children are in fact not tested or authorised on children. The improvement to the health of children in Europe is said to be likely to come from better research, development and authorisation of paediatric medicines. The new Regulation creates a new system through various strategies, which are stated as aimed at achieving better availability of paediatric medicines throughout the Community and removing obstacles to trade of medicinal products within the Community.

As well as dealing with the appropriate standards of research, clinical trial, and authorisation, the Regulation also looks to improve information on the use of paediatric medicines. Obligation in this area are to be accompanied by certain incentives created in the Regulation.

Of particular interest is the incentive with respect to medicines still protected by monopoly (patent or supplementary protection certificate (SPC)). The Regulation introduces new obligations to submit (as part of the procedure for market authorisation) results of clinical studies in accordance with a paediatric investigation plan or proof of a waiver where the medicines of no paediatric use. These obligations are accompanied by an incentive in the form of the extension of exclusive rights (an additional 6 months) on the basis that it takes longer to test and authorise paediatric medicines. In the case of SPCs, extensions are available only for products authorised in all Member States and for which marketing authorisation procedures are complete.

In the drafts leading to final text, discussions rejected proposals to exclude extensions for products that have already received the protection of data or market exclusivity for the same paediatric use in the EU. Similarly, the Commission rejected earlier drafts seeking to amend the proposed text to exclude an extension of the SPC for products that have already benefited from patent protection covering the paediatric use. The Commission claimed that such exclusions would compromise the policy objective of encouraging greater research into medicines for children. Nevertheless, in keeping with this rationale, importantly the extensions are available as an incentive only for research entered into after the new Regulation has entered into force.

However, in May this year, the European Court of Justice (ECJ) ruled out SPCs for new formulations of known active ingredients, in the Massachusetts Institute of Technology (C-431/04). This was despite an earlier opinion of the Advocate-General. The Court ruled: "Article 1(b) of the Regulation must be interpreted so as not to include in the concept of 'combination of active ingredients of a medicinal product' a combination of two substances, only one of which has therapeutic effects of its own for a specific indication, the other rendering possible a pharmaceutical form of the medicinal product which is necessary for the therapeutic efficacy of the first substance for that indication." This may limit the incentive in respect of extensions of SPCs for new uses (paediatric) of known products.

Regarding off-patent paediatric medicines, the Regulation introduces a new kind of marketing authorisation, referred to as the Paediatric Use Marketing Authorisation (PUMA). Such medicines must have been appropriately tested for paediatric use. The Regulation also includes provisions on the funding of research into the use of off-patent medicines for paediatric purposes.

Medicinal products for the treatment of serious diseases affecting fewer than 5 in 10 000 people in the Community are often referred to as "orphan drugs," because of their limited interest to the pharmaceutical industry. The Orphan Drug Regulation currently provides for 10 years market exclusivity, in order to provide incentives to bring such treatments to market, which the new Regulation is expected to extend to 12.

The Regulation also creates a new scientific committee, an expert committee within the European Medicines Agency (EMEA). This Committee will be primarily responsible for the assessment and agreement of paediatric investigation plans and waivers (described above).

The new Regulation amends 3 European instruments - Council Regulation (EEC) No 1768/92 creating supplementary protection certificate; Regulation (EC) No 726/2004 for authorisation and supervision of medicinal products for human and veterinary use (establishing the EMEA); and the Clinical Trials Directive 2001/20/EC. The original proposal text and amended text are available. The text of the adopted Regulation is likely to be published in the Official Journal in the next couple of weeks.